

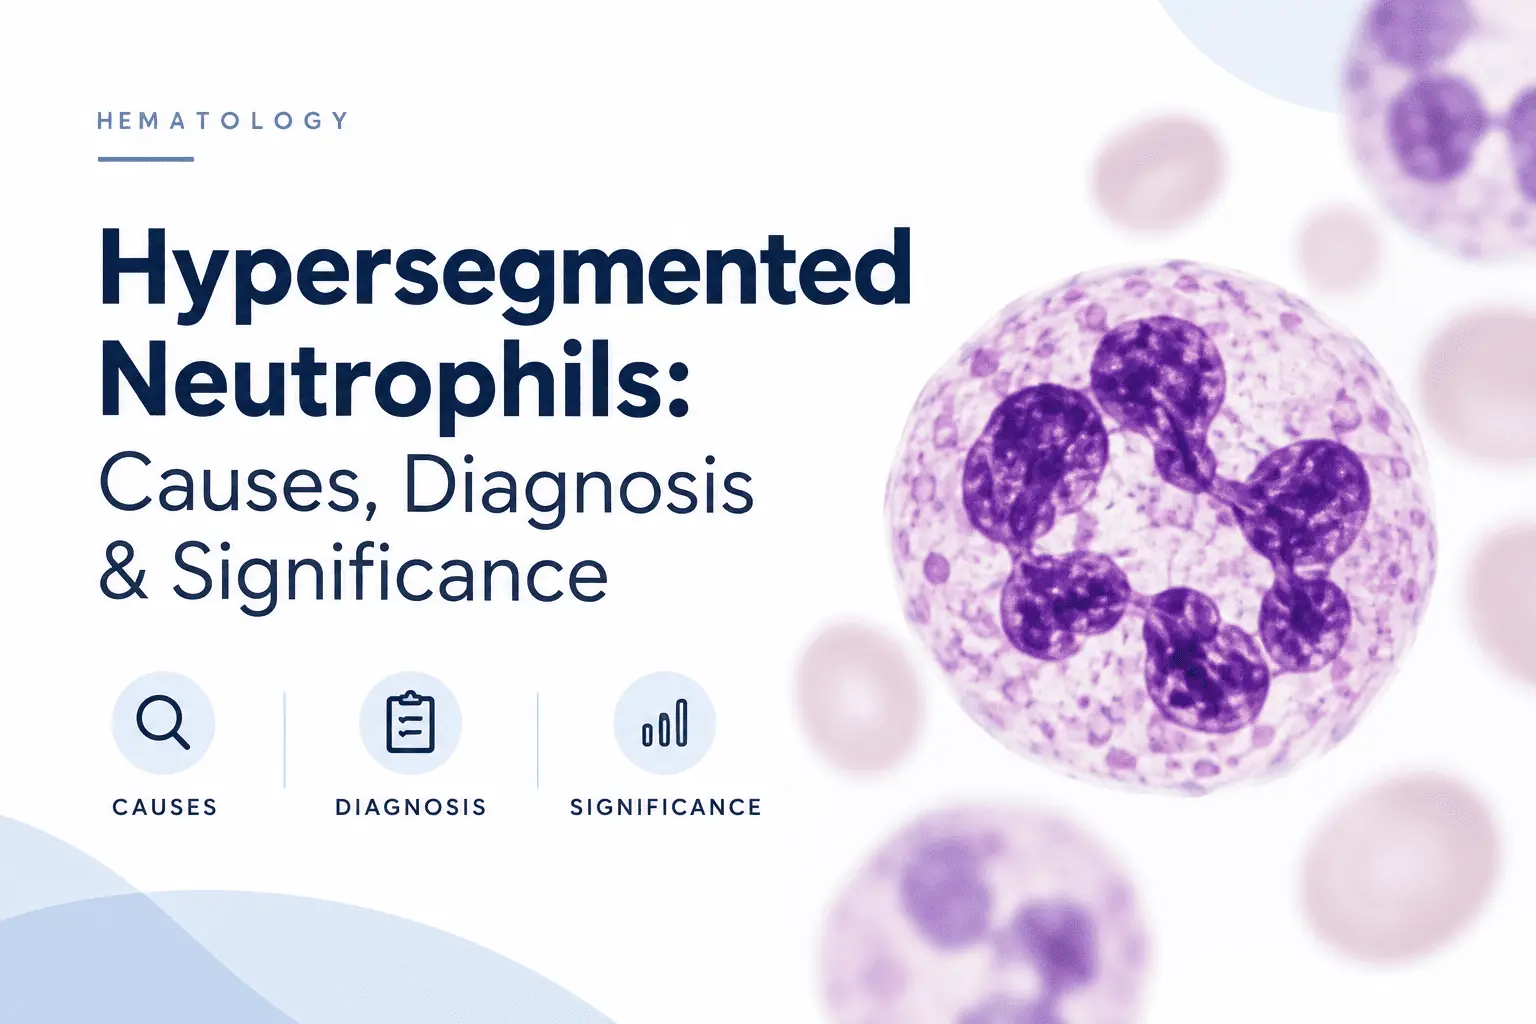
Hypersegmented neutrophils are mature neutrophils with an unusually high number of nuclear lobes. They are most strongly associated with megaloblastic changes caused by vitamin B12 or folate deficiency, but they can also occur in other hematological and clinical conditions.
Because these cells can be identified on a routine peripheral blood smear, their presence may provide an early clue to an underlying disorder of blood-cell production. However, hypersegmentation is a morphological finding rather than a diagnosis by itself. Its significance depends on the patient’s complete blood count, other blood-film findings, clinical history, and laboratory results.
This article explains what hypersegmented neutrophils look like, why they develop, the conditions associated with them, how they are diagnosed, and what their presence means for patient management.
1. What Are Hypersegmented Neutrophils?
Morphology and Characteristics
Neutrophils are white blood cells belonging to the innate immune system. In a normal peripheral blood smear, a mature neutrophil typically has a segmented nucleus containing three to five lobes connected by thin strands of chromatin.
A neutrophil becomes described as hypersegmented when its nucleus contains an abnormally large number of lobes. Common morphological definitions include the presence of a neutrophil with six or more nuclear segments, or an increased proportion of neutrophils containing five segments. Exact counting criteria can vary between laboratory references.
Under the microscope, hypersegmented neutrophils generally retain the characteristic cytoplasmic appearance of mature neutrophils, but their nuclei appear unusually divided or “over-segmented.”
They may also appear somewhat larger than normal neutrophils when they occur as part of a megaloblastic process.
Why Do Hypersegmented Neutrophils Form?
The key mechanism involves abnormal DNA synthesis during hematopoiesis.
Neutrophil precursors normally undergo repeated nuclear divisions as they mature in the bone marrow. When DNA synthesis is impaired, nuclear maturation becomes abnormal. The nucleus does not mature and divide normally, while cytoplasmic maturation can continue. This produces cells with unusually mature-looking, highly segmented nuclei.
This phenomenon is particularly characteristic of megaloblastic hematopoiesis, in which impaired DNA synthesis affects multiple blood-cell lineages. Vitamin B12 and folate are essential for nucleotide metabolism and DNA synthesis, which explains why deficiencies of these vitamins can produce this characteristic blood-film abnormality.
The same underlying disturbance can produce other morphological abnormalities, including macro-ovalocytes, anisopoikilocytosis, and abnormalities affecting red-cell and platelet production.
Comparison With Normal and Dysplastic Neutrophils
| Feature | Normal neutrophil | Hypersegmented neutrophil | Dysplastic neutrophil |
|---|---|---|---|
| Nuclear segmentation | Usually 3–5 lobes | Excessive segmentation | Abnormal segmentation or nuclear morphology |
| Nuclear appearance | Regular, mature | Highly lobulated | May show abnormal shape, chromatin, or segmentation |
| Typical context | Normal blood | Often megaloblastic hematopoiesis | May occur with disorders such as myelodysplastic syndromes |
| Diagnostic meaning | Normal finding | Clue to an underlying condition | May indicate abnormal hematopoiesis |
It is important not to equate hypersegmentation with dysplasia automatically. Hypersegmentation is most classically associated with megaloblastic changes, whereas myelodysplastic syndromes (MDS) can produce a broader range of abnormalities across blood-cell lineages. Hypersegmented neutrophils can occur as a dysplastic feature in MDS, but they are not specific for it.
2. Causes of Hypersegmented Neutrophils
The causes can be broadly divided into nutritional deficiencies, hematological disorders, and less common conditions or circumstances.
Vitamin Deficiencies
The most important causes are deficiencies of:
- Vitamin B12 (cobalamin)
- Folate (vitamin B9)
Both vitamins are required for normal DNA synthesis. Their deficiency can therefore interfere with the production and maturation of rapidly dividing bone-marrow cells.
Vitamin B12 deficiency may result from inadequate dietary intake, impaired absorption, autoimmune pernicious anemia, gastrointestinal disorders, or certain medications. Folate deficiency can be associated with inadequate intake, malabsorption, increased physiological requirements, alcohol use, and some medications.
In megaloblastic anemia, hypersegmented neutrophils commonly occur together with macro-ovalocytes and macrocytosis.
Hematological Disorders
Hypersegmentation can also be encountered in some disorders affecting hematopoiesis.
Myelodysplastic syndromes may produce abnormal neutrophil morphology as part of broader dysplasia. In this setting, the blood smear usually contains additional abnormalities, and the diagnosis cannot be established from neutrophil morphology alone.
Rarely, hereditary neutrophil hypersegmentation can produce persistent hypersegmented neutrophils without the typical nutritional deficiency underlying megaloblastic anemia.
Hypersegmentation has also been described in association with certain non-megaloblastic conditions, including some cases of iron deficiency and renal disease. These associations are less characteristic than vitamin B12 or folate deficiency and should be interpreted in the context of the entire blood picture.
Other Possible Causes
Medication history can be important when investigating abnormal blood-cell morphology. Several drugs can interfere with folate metabolism, DNA synthesis, or bone-marrow function and may produce macrocytosis or megaloblastic changes. These include certain antimetabolite, antimicrobial, anticonvulsant, and chemotherapeutic drugs.
Consequently, the finding of hypersegmented neutrophils should not lead directly to a single diagnosis. The patient’s medications, nutritional history, gastrointestinal history, alcohol exposure, and other laboratory findings should all be considered.
3. Diagnostic Approach: Identifying Hypersegmented Neutrophils
Peripheral Blood Smear Examination
The peripheral blood smear is central to recognizing hypersegmented neutrophils.
A laboratory professional or hematologist examines stained blood cells under a microscope and evaluates:
- Nuclear segmentation of neutrophils
- Red-cell size and shape
- Presence of macro-ovalocytes
- Anisocytosis and poikilocytosis
- Platelet morphology
- Other white-cell abnormalities
- Evidence of immature or dysplastic cells
The combination of macrocytosis, macro-ovalocytes, and hypersegmented neutrophils strongly suggests a megaloblastic process and can help distinguish it from several non-megaloblastic causes of macrocytosis.
A blood smear should therefore be interpreted together with the complete blood count rather than as an isolated observation.
Laboratory Tests
Once hypersegmentation is identified, laboratory testing is used to determine whether an underlying nutritional or hematological disorder is present.
The initial evaluation commonly includes:
- Complete blood count (CBC)
This establishes whether anemia, leukopenia, thrombocytopenia, or macrocytosis is present. - Mean corpuscular volume (MCV)
An elevated MCV supports macrocytosis, although vitamin B12 deficiency can occasionally occur without obvious macrocytosis. - Serum vitamin B12
- Serum folate
- Reticulocyte count
This provides information about bone-marrow red-cell production.
Depending on the results, additional biochemical testing may be useful. When vitamin B12 status is uncertain, methylmalonic acid (MMA) can help identify tissue-level B12 deficiency, particularly when the serum B12 concentration is borderline. Homocysteine can also be elevated in both B12 and folate deficiency and therefore has different interpretive implications.
Additional Tests for Underlying Causes
Identifying the abnormal neutrophil is only the first step. The next objective is determining why the abnormality developed.
When vitamin B12 deficiency is confirmed or strongly suspected, additional evaluation may be necessary to distinguish inadequate intake from impaired absorption. Depending on the clinical context, this can include investigation for pernicious anemia, gastrointestinal disease, previous gastrointestinal surgery, or medication-associated deficiency. Recent clinical guidance also describes testing for intrinsic-factor antibodies and other causes of impaired absorption when the cause is unclear.
If nutritional deficiencies are excluded and the blood count shows persistent cytopenias or multiple morphological abnormalities, evaluation for a bone-marrow disorder may be appropriate. In selected patients, this can lead to bone marrow examination and additional hematological testing.
4. Clinical Significance and Implications
Diagnostic Importance
Hypersegmented neutrophils are valuable because they can provide a morphological clue to abnormal DNA synthesis before the underlying cause has been fully established.
Their greatest diagnostic importance is in the recognition of megaloblastic hematopoiesis. When they occur alongside macro-ovalocytes and macrocytosis, the combination should prompt evaluation for vitamin B12 or folate deficiency.
However, hypersegmentation is not sufficiently specific to establish the cause on its own. A patient should not be diagnosed with vitamin deficiency solely because hypersegmented neutrophils are seen on a blood smear.
Prognostic Value
Hypersegmented neutrophils generally have limited independent prognostic value.
Their clinical importance comes primarily from what they reveal about the underlying process. For example, identifying megaloblastic changes may lead to the diagnosis of a correctable nutritional deficiency, while persistent abnormalities accompanied by other cytopenias may prompt investigation for an underlying bone-marrow disorder.
In vitamin B12 deficiency, the consequences of delayed diagnosis can extend beyond anemia because neurological manifestations may develop and can become persistent if deficiency is prolonged.
Thus, the finding is better considered a diagnostic signal than a standalone marker of disease prognosis.
Implications for Treatment and Management
The management implications depend entirely on the underlying cause.
If the finding reflects vitamin B12 or folate deficiency, treatment focuses on correcting the deficiency and identifying why it occurred. If a medication is responsible for impaired folate metabolism or bone-marrow function, the medication regimen may need to be reviewed by the treating clinician.
When the abnormality occurs as part of a suspected marrow disorder, further hematological evaluation may be required.
One important clinical principle is that vitamin B12 deficiency should be excluded before treating unexplained megaloblastic anemia with folate alone. Folate can improve the hematological abnormalities while allowing neurological damage from untreated B12 deficiency to continue.
Public Health and Preventive Measures
Some causes of hypersegmented neutrophils are preventable or can be detected early.
Adequate intake of vitamin B12 and folate is important, particularly for individuals whose diets or medical conditions put them at risk of deficiency. People following restrictive diets may require particular attention to reliable sources of vitamin B12, while folate requirements increase during pregnancy.
Food fortification and folic acid supplementation around pregnancy have also played an important public-health role in reducing folate deficiency and preventing neural tube defects.
Prevention, however, should not be reduced to dietary intake alone. Conditions that impair vitamin absorption can cause deficiency even when dietary intake appears adequate.
5. Treatment and Management
Correcting Vitamin Deficiencies
Treatment should be directed at the specific deficiency identified through laboratory evaluation.
Vitamin B12 deficiency is treated with vitamin B12 replacement. Oral treatment is effective for many patients, while parenteral treatment may be preferred in some situations, particularly severe deficiency, significant neurological manifestations, or specific absorption problems.
Folate deficiency is generally treated with oral folate supplementation while the underlying reason for the deficiency is addressed.
The distinction between the two deficiencies is important because their treatment is not interchangeable. In particular, folate should not be used as a substitute for vitamin B12 when B12 deficiency has not been excluded.
Managing Non-Nutritional Causes
When hypersegmentation is not caused by nutritional deficiency, treatment depends on the underlying condition.
For medication-associated abnormalities, clinicians may review the dose, duration, or necessity of the suspected drug and consider alternatives when appropriate.
If the blood smear and CBC suggest a bone-marrow disorder such as myelodysplastic syndrome, management requires hematological evaluation rather than vitamin supplementation alone.
Rare hereditary forms of neutrophil hypersegmentation may require a different approach, particularly when the abnormal morphology persists despite normal nutritional studies and there is no evidence of acquired disease.
Dietary and Lifestyle Recommendations
Diet can contribute to maintaining adequate vitamin status, but dietary advice should be individualized according to the cause of deficiency.
Sources of folate include leafy green vegetables, legumes, fruits, fortified foods, and other folate-containing foods.
Sources of vitamin B12 include meat, fish, eggs, dairy products, and fortified foods. People who consume little or no animal-derived food may need fortified foods or supplementation to maintain adequate B12 intake.
Dietary changes alone may not correct deficiency when absorption is impaired. For example, pernicious anemia and some gastrointestinal disorders can interfere with B12 absorption regardless of dietary intake.
Monitoring and Follow-Up
Follow-up should assess both the blood abnormality and the underlying cause.
Depending on the diagnosis, monitoring may include:
- Repeat CBC
- MCV assessment
- Reticulocyte response
- Repeat vitamin B12 or folate testing when appropriate
- MMA or other biochemical markers in selected B12-deficient patients
- Assessment of neurological symptoms when B12 deficiency is present
- Follow-up of the underlying gastrointestinal, hematological, or medication-related cause
The hematological response can occur relatively quickly after effective treatment. In vitamin B12 deficiency, for example, the reticulocyte response may begin within approximately one week, while complete correction of hematological abnormalities can take several weeks. Neurological recovery, when neurological injury has occurred, may take considerably longer and can be incomplete when treatment is delayed.
Persistent hypersegmented neutrophils or continued macrocytosis despite appropriate treatment should prompt reassessment of the diagnosis, treatment adherence, absorption, and the possibility of another underlying disorder.
Medical Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice. It is not intended to replace professional medical consultation, diagnosis, or treatment. Always seek the advice of a qualified healthcare provider with any questions regarding a medical condition.
References and Further Reading
- Kaferle J, Strzoda CE. Evaluation of macrocytosis. Am Fam Physician. 2009 Feb 1;79(3):203-8.
- Infante M, Leoni M, Caprio M, Fabbri A. Long-term metformin therapy and vitamin B12 deficiency: An association to bear in mind. World J Diabetes. 2021 Jul 15;12(7):916-931. doi: 10.4239/wjd.v12.i7.916.
- Lynch EC. Peripheral Blood Smear. In: Walker HK, Hall WD, Hurst JW, editors. Clinical Methods: The History, Physical, and Laboratory Examinations. 3rd ed. Boston: Butterworths; 1990. Chapter 155.
- Bizzaro N, Antico A. Diagnosis and classification of pernicious anemia. Autoimmun Rev. 2014 Apr-May;13(4-5):565-8. doi: 10.1016/j.autrev.2014.01.042.
- Parakh N, Dewan P. Revisiting the hematological manifestations of vitamin B12 deficiency. Front Nutr. 2026 Aug 12;13:1898533. doi: 10.3389/fnut.2026.1898533.
- Tran PN, Tran MH. Cobalamin deficiency presenting with thrombotic microangiopathy (TMA) features: A systematic review. Transfus Apher Sci. 2018 Feb;57(1):102-106. doi: 10.1016/j.transci.2018.01.003.
- Lodge-Rigal RD, Novotny DB. Hypersegmentation of neutrophils in the cerebrospinal fluid: report of a case with hematologic correlation and review of the literature. Diagn Cytopathol. 1994;11(1):56-9. doi: 10.1002/dc.2840110113.
- Hash RB, Sargent MA, Katner H. Anemia secondary to combined deficiencies of iron and cobalamin. Arch Fam Med. 1996 Nov-Dec;5(10):585-8. doi: 10.1001/archfami.5.10.585.


